News
131 entries in total
The recurrence of an originally undiagnosed polymyalgia rheumatica (PMR) 6 years after its first symptoms occurrence
Polymyalgia rheumatica (PMR) is one of the most common rheumatic diseases diagnosed in people over 50 years of age. Its incidence increases with age, reaching a peak at 72-73 years of age (PMR is rarely diagnosed in the 50-year-old population) [1]. Statistically, it affects women twice as often. A greater predisposition is also observed in the white race [2]. In Europe, the incidence is on average 1 in 133 people over 50 years of age [3]. There is also a clear geographical variation – the vast majority of diagnoses occur in Northern European countries, particularly Sweden, while in Southern Europe, for example, in Italy, it is much less frequently diagnosed. The etiology of the disease has not been fully elucidated. It is assumed that autoimmune processes underlie it. The role of solar radiation and viral infections has also been suggested [2]. Typical symptoms of polymyalgia include pain and stiffness in the neck, shoulder girdle, and hip muscles [1,2]. PMR belongs to a group of inflammatory diseases with an immune basis. Its etiology also includes a genetic predisposition, including the involvement of antigens: HLA-DR4, HLADRB1*04, and proinflammatory cytokines: TNFα and IL6. Some studies have also demonstrated reduced secretion of adrenal cortex hormones (cortisol, dehydroepiandrosterone) in individuals affected by this condition [4]. The variety of factors postulated to play a significant role in the development of PMR indicates the need for further research into the etiology of this disease.

Abstracts - ESPES (European Society of Paediatric Endoscopic Surgeons) 7th Annual Congress
It is my great pleasure to present a special edition of our Journal, printed for the occasion of the 7th Annual Congress of the European Society of Paediatric Endoscopic Surgeons (ESPES)! In this issue you can find regular case reports submitted to the Journal and all abstracts of ESPES 2017 Congress (September 27th — 29th Wroclaw, Poland). Professor Dariusz Patkowski, a member of our Scientific Council, is the Congress Chairman. All abstracts will be also available after Congress on the journal’s website — www.MDcase.net.

Intrauterine growth restriction in the course of Silver-Russell syndrome - a case report
<p>Intrauterine fetal growth restriction (IUGR) is one of the most serious complications of pregnancy. It affects an average of 8% of live-born newborns in developed countries, and up to 15-20% in developing countries[1, 2, 3].</p><p>It is associated with an increased rate of intrauterine deaths and pregnancy complications, including preterm deliveries and perinatal deaths. In children, abnormalities in psychophysical development and a higher incidence, including in adulthood, of conditions such as obesity, diabetes, and metabolic syndrome are observed[1, 2, 7, 8 , 9]. IUGR refers to the inability of the fetus to reach its full growth potential during intrauterine life [4, 5, 6]. Many times the term hypotrophy is used interchangeably. According to most authors, IUGR is diagnosed when two ultrasound measurements of the fetus show excessively slow growth rates and/or when birth weight/length is less than 2 SD ( standard deviations), or 10th percentile relative to gestational age. In severe forms, birth weight or AC ( abdominal circumference) correspond to values below the 3rd Centile. [6, 8]. The etiology of intrauterine growth retardation is multifactorial, and despite advances in medicine, it is often, even in 40%, impossible to identify . We distinguish maternal causes ( among others.: hypertension, kidney disease, cardiovascular disease, diabetes mellitus, thrombophilias, antiphospholipid syndrome, genetic factors, drugs), fetal(mainly genetic abnormalities, congenital malformations, intrauterine infections, metabolic blocks), placental (abnormalities in placental structure and capacity, pre-eclampsia), environmental (low socioeconomic status of the mother, stimulants, nutritional deficiencies) [1, 9, 10, 11, 12].</p><p>The management of suspected IUGR should include a thorough general medical and obstetric history, assessment of risk factors to identify pregnant women requiring enhanced surveillance, and detailed imaging and laboratory tests. Ultrasonography of the fetus (evaluation of anatomy, size , proportion, growth dynamics) is the primary diagnostic test. It is also necessary to monitor fetal well-being with cardiotocography (ktg), assessment of blood flow in selected vessels ( usg doppler), amniotic fluid volume and biophysical profile. Appropriate laboratory tests are performed to confirm or exclude maternal chronic diseases, intrauterine infections, pre-eclampsia, HELLP syndrome and other pregnancy pathologies that may affect growth disorders [12,13]. In the absence of a clear cause leading to IUGR, genetic testing is important. Maternal genes are believed to have a major impact on the baby's birth weight. However, also many chromosomal aberrations in the fetus are associated with intrauterine growth retardation [6, 12]. An example is Silver- Russell syndrome (SRS), which varies widely in the type of genetic alterations present and how they are inherited. Mutations affect chromosome 11, 7, among others, and are associated with characteristic phenotypic features, which include primarily bone lesions in the form of : scoliosis, limb length disproportion, toe fusion, elbow joint lesions. According to the literature, between 1:50,000 and 1:100,000 children are born with this syndrome [14, 15, 16].</p><p>The main goal of maternal and child care in pregnancy complicated by intrauterine fetal growth retardation is to ensure and strictly assess fetal well-being and to choose the optimal delivery date [6, 12].</p>.

Tongue cancer diagnosed incidentally in a patient with anaemia and joint pain.
Tongue cancer is the most common oral cancer [1]. Most patients report exposure to known risk factors for cancer development, such as frequent alcohol consumption, smoking, and poor oral hygiene [1, 2]. Unfortunately, due to the tumor's location and patients' failure to appreciate early symptoms, most diagnoses are made in very advanced stages of the disease [2]. We present a case report of a patient with incidentally diagnosed tongue cancer.
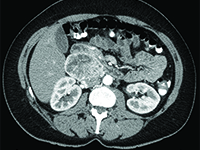
Paraganglioma in a 41-years old woman: a rare neoplasm of the retroperitoneal space
<p>Paraganglioma(Latin: paraganglioma) is a rare, mostly benign neuroendocrine tumor originating from the paraventricular bodies of the parasympathetic and sympathetic nervous systems. The 2013 National Cancer Registry did not find any data on the incidence of this tumor in Poland [1]. The histopathological structure and symptoms of the tumor often resemble pheochromocytoma. It can be said that pheochromocytoma is a special type of chaperone tumor. Chaperones originating from the parathyroid bodies of the parasympathetic nervous system are usually located near the large vessels of the head and neck (bifurcation of the common carotid artery-the most common location) [2], while chaperones from the sympathetic nervous system chaperones occur along the sympathetic trunk located adjacent to the vertebral column, abdominal aorta and inferior vena cava [even aortic glomerulus (Zuckerkandel's organ) lying on either side of the aorta, just above its bifurcation-the most common location].</p><p>Parenomas are neoplasms of old age, with peak incidence in the 5th and 6th decades of life. In about 10% of cases, they occur familially, being part of such genetically determined syndromes as [3]:</p><p>- von Hippel-Lindau syndrome</p><p>- multiple endocrine adenocarcinoma syndrome types 2A and 2B</p><p>- Carney syndrome</p><p>Diagnosis of chaperones is not straightforward, as these tumors are rare. In cases where the tumor is hormonally active, there are symptoms associated with high levels of catecholamines in the blood (accelerated heart rate, increased blood pressure, hot flashes, headaches). When a hormonally active tumor is absent, symptoms may result from tumor growth in a specific location (dull pain in the lumbar region). Most often, however, chaperones are diagnosed incidentally in a neck or abdominal and pelvic ultrasound performed for other reasons or as an annual prophylaxis (the tumor diagnosis is then confirmed on CT).</p><p>Tumor fine-needle biopsy is unlikely to be performed due to the rich vascularization of the tumor and the associated risk of bleeding.</p><p>Because of the rarity of chaperones, there are no established diagnostic and therapeutic algorithms.</p><p>Treatment consists of surgical removal of the tumor. In cases where the location of the tumor does not allow surgical removal, radiation therapy is applicable.</p><p></p><p>Rocalization is generally very good. If the tumor is completely removed, the cure is complete.</p>
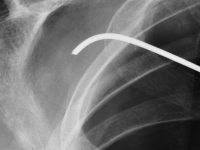
A foreign body in the chest
Patients with pneumothorax constitute a significant percentage of all hospitalizations in general surgery departments. Pneumothorax can be spontaneous, most often caused by pulmonary emphysema, or post-traumatic, primarily resulting from chest wall contusion. A specific type of pneumothorax is the iatrogenic variety, which can generally be classified as post-traumatic.
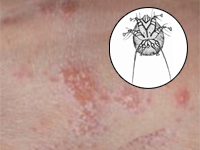
Severe scabies misdiagnosed as allergic reaction after kidney transplantation.
Due to immunosuppressive therapy, paƟents who underwent organ allotransplantaƟon are more likely to present an unusual clinical manifestaƟon of frequent everyday diseases. We present an uncommon case of Scabies in the renal transplanted recipient.
Cerebellar-extrapyramidal syndrome as unusual manifestation of Gitelman syndrome in siblings
It’s a case presentaƟon of two siblings: a 17-year-old girl and her 15-year-old brother who both developed speech and swallowing difficulƟes, shaking hands and decreased muscle tone at the age of 4. Results of laboratory tests only indicated a tendency to low potassium and magnesium serum concentraƟons. The siblings were diagnosed for cerebellar-extrapyramidal syndrome. AŌer several years of follow-up the paƟent were referred to the Pediatric Nephrology Hospital because of hyperechogenic reflecƟons from renal parenchyma in abdominal ultrasound. Finally, tubulopathy was diagnosed. Diet supplements was included as a result of a persistent electrolyte imbalance, with a posiƟve therapeuƟc effect.
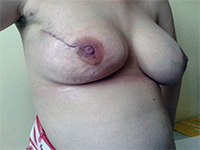
Breast cancer in pregnancy – a proposal of surgical treatment with immediate reconstruction of breast
Breast cancer in pregnant women includes cases in which breast cancer develops during pregnancy or within 12 months of delivery and occurs in 1 to 3 in 10,000 pregnancies, representing 0.2–4% of all breast cancers [1]. Statistically, it most often occurs in women aged 50–69 years, while it is not common in women under 40 years of age. However, recent observations indicate an increase in the number of breast cancer cases diagnosed before menopause [2]. The trend in the incidence in premenopausal women (20–49 years of age) is upward, and over the last three decades, the incidence in this age group has almost doubled [3]. This indicates an increase in the number of cases due to the clearly visible tendency to become pregnant later in the reproductive years. The average age of breast cancer patients at the time of pregnancy is 33 years [4]. An increased risk of developing the disease also applies to women who carry constitutive mutations in the BRCA1 gene and those with a family history of breast cancer. Diagnosis and treatment of cancer patients during pregnancy are difficult due to nonspecific symptoms overlapping with pregnancy-related ailments and symptoms. Once a cancer diagnosis is confirmed, decisions regarding further treatment should be aimed at both optimal maternal treatment and maintaining normal fetal development [5].
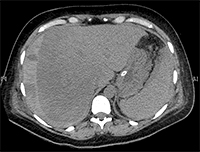
Application of Methods of Invasive Radiology in Treatment of Liver Rupture in Woman after Delivery with HELLP Syndrome
Liver diseases in pregnancy are rare. They are divided into pregnancy-related diseases, i.e., induced by pregnancy, and pregnancy-independent diseases, occurring as standalone conditions [2].<br />In addition to HELLP syndrome, pregnancy-related diseases include: hyperemesis gravidarum, intrahepatic cholestasis of pregnancy, preeclampsia and eclampsia, and acute fatty liver atrophy. These conditions affect and complicate approximately 5.5% to 13.5% of pregnancies. Preeclampsia, eclampsia, HELLP syndrome, and their complications, such as hepatic infarction and liver rupture/hematoma, are associated with hypertension in pregnancy. The most common conditions are preeclampsia and eclampsia, which affect 5-10% of pregnancies, and approximately 5% to 10% of these develop HELLP syndrome [3-5]. It is estimated to occur in approximately 6 pregnant women per 1000 pregnancies [2].<br />The concept and creation of the acronym HELLP (H = hemolysis, EL = increased liver enzyme levels in the blood, LP = decreased platelet levels) was introduced by Louis Weinstein, who in 1982 presented the results of an analysis of a group of pregnant women with highly pronounced consequences of preeclampsia and eclampsia [2,6]. The researcher showed that all patients had hemolytic anemia associated with microangiopathy, changes in the shape of erythrocytes in the peripheral smear, moderate to severe thrombocytopenia, and abnormal enzymatic tests of liver function, usually in combination with epigastric pain, nausea and vomiting, and severe hypertension and proteinuria often coexisted with these symptoms [3,6]. Since the publication of L. Weinstein's work, others have made significant research contributions to understanding the pathogenesis, natural history, clinical spectrum, classification, and management strategies for this syndrome [3].<br />HELLP syndrome typically develops suddenly in the 2nd or 3rd trimester of pregnancy or within 48 hours of delivery [5,7,8]. It usually accompanies preeclampsia/eclampsia, but can also occur independently. As in the aforementioned conditions, the likely cause of the syndrome is abnormal placental development and ischemia, which induce oxidative stress, resulting in the release of factors that systematically damage the vascular endothelium through platelet activation, vasoconstriction, and loss of the typical pregnancy-related relaxation of vascular smooth muscle [3,9-13].<br />The liver plays a central role in the pathogenesis of HELLP syndrome and is key to understanding the nature of the disorder. Dysfunction and death of perihepatic hepatocytes in a given patient likely correlates with the severity of the condition. The previously discovered CD95 protein (APO-1, FAS), which plays an important role in the pathogenesis of liver disease, mediates hepatocyte apoptosis by binding to Fas-ligand protein (a ligand for the Fas receptor), a member of the TNF receptor family. Fas-ligand is produced by the placenta, and its serum levels increase during the course of the disease and correlate with its severity. Blocking CD95 signaling reduces serum hepatocytotoxic activity in HELLP syndrome [15].<br />This model of HELLP syndrome pathophysiology has been confirmed by other studies, demonstrating that the liver is the target and the placenta is the initiator of the disorders [3].<br />Many authors emphasize the similarity of HELLP syndrome to the Systemic Inflammatory Response Syndrome (SIRS), which may be evidenced by high levels of inflammatory mediators in serum and liver tissues and clinically available laboratory parameters such as the level of leukocytosis, which increases proportionally to the advancement of the disease [15-17].<br />Currently, there are two basic laboratory classification systems for HELLP syndrome: Mississippi and Tennessee, which were created for the purposes of diagnosis, assessment of disease advancement, and evaluation of treatment efficacy [2,3]. Considered separately, they also provide a platform for comparison of research results. They were developed in the 1980s at the research centers of the Universities of Tennessee and Mississippi.<br />The Mississippi classification takes into account the values of three basic parameters measured in blood serum: platelets, liver enzymes - AST and ALAT, and lactate dehydrogenase - LDH, which correlates with the intensity of hemolysis. Classification is ultimately determined by the lowest platelet count in the course of the disease. Grade 1 is associated with the most severe form of the disease, and grade 3 with the mildest. In this classification, all three parameters must be abnormal to diagnose HELLP syndrome.<br /><br />Mississippi Classification:<br />1. Platelet count 50,000, AST and/or ALAT 70 IU/L, LDH 600 IU/L<br />2. Platelet count 100,000, AST and/or ALAT 70 IU/L, LDH 600 IU/L<br />3. Platelet count 150,000, AST and/or ALAT 40 IU/L, LDH 600 IU/L<br /><br />The second classification system that has become common is the Tennessee classification. It defines the so-called true (complete) and incomplete (partial) HELLP syndrome.<br /><br />Tennessee classification:<br />1. Complete HELLP syndrome: platelet count 100,000, AST 70 IU/L; LDH 600 IU/L or bilirubin 1.2 mg/% and abnormal erythrocyte count